


Article Key Points:
- At ESC 2026, Prof. Jing Gao’s team from Tianjin Chest Hospital presented a prospective cohort of 1220 premature myocardial infarction (PMI) patients (men ≤45, women ≤55) undergoing PCI, with a median follow-up of 582 days and an overall MACE incidence of 11.1% (136/1220).
- After adjustment for traditional risk factors, elevated homocysteine (Hcy ≥15 μmol/L) independently predicted MACE with an adjusted hazard ratio of 2.72 (95% CI 1.87-3.95; P<0.001).
- Hcy showed synergistic amplification with metabolic and inflammatory markers: combining elevated Hcy with elevated D-dimer, lipoprotein(a), or hs-CRP raised MACE risk to 3.13- to 4.12-fold compared with normal Hcy.
- Combining elevated Hcy with obesity (BMI ≥28) escalated MACE risk to 6.54-fold (95% CI 3.01-14.20; P<0.001); three-factor combinations with obesity plus D-dimer or hs-CRP further escalated risk to 9.91-fold and 17.51-fold, respectively.
- The authors note that the high-risk subgroups identified here may represent populations most likely to benefit from Hcy-lowering interventions, though the study is single-center with limited three-factor subgroup sample sizes and 19-month median follow-up.
A simple laboratory test may help predict long-term outcomes in young patients with premature myocardial infarction (PMI)—who are typically middle-aged or younger (men ≤45, women ≤55) and whose long-term prognosis is shaped by a constellation of metabolic and inflammatory factors. Homocysteine (Hcy), a metabolite with pro-inflammatory and pro-thrombotic activity, has been shown to contribute to the development of atherosclerosis; however, its independent effect on long-term outcomes in PMI patients—and its joint action with obesity and inflammatory markers—had not previously been systematically evaluated. A prospective cohort study from Prof. Jing Gao’s team at Tianjin Chest Hospital, China, presented at the 2026 European Society of Cardiology (ESC) Congress, addressed this gap. The results showed that Hcy is not only an independent predictor of long-term major adverse cardiovascular events (MACE) in PMI patients but also interacts with obesity and inflammatory status, further amplifying the adverse prognostic impact of these risk factors.
Expert Profile:
Prof. Jing Gao

- Current academic and clinical title, department, and institution: PhD, postdoctoral fellow; Level 2 chief physician and researcher; Tianjin Chest Hospital
- Doctoral or postdoctoral supervisory role: Doctoral and postdoctoral supervisor
- Leadership role in a professional group or medical association: Lead, Tianjin “131” Innovative Talent Team; first-tier candidate, Tianjin “131” Innovative Talent Cultivation Program; “Jinmen Medical Talent” of Tianjin’s first high-level health talent program; “Most Beautiful Science and Technology Worker” of Tianjin Health System; “Outstanding CPC Member” under the Tianjin Health System “Two Excellences, One Priority” Recognition Program; Committee Member, Atherosclerosis Group, 6th Committee of Cardiovascular Medicine Branch, Chinese Medical Doctor Association; Vice Lead, Beijing-Tianjin-Hebei Biobank Resource Collaboration Group, Clinical Data and Sample Resource Committee, Chinese Research Hospital Society; Vice Chair (Tianjin), Beijing-Tianjin-Hebei Biobank Alliance; National Committee Member, Biobank Branch, China Medicinal Biotechnology Association; Vice Chair, Basic Research Committee, Cardiovascular Medicine Branch, Tianjin Medical Doctor Association; Council Member, Tianjin Heart Society; Committee Member, Cardiovascular Disease Branch, Tianjin Medical Association; Expert, National Science and Technology Plan Expert Database; Reviewer, National Health Commission major science and technology projects; Reviewer, National High-level Medical Talent Programs; Reviewer, Ministry of Education High-level Talent Programs; Reviewer, China Academic Degrees and Graduate Education Development Committee; Designated Expert, Expert Service at the Grassroots Program, Ministry of Human Resources and Social Security; Reviewer, China Postdoctoral Science Foundation; Reviewer, Science and Technology Expert Databases of Shanghai, Tianjin, Heilongjiang, Guizhou, and Sichuan
- Hospital, department, laboratory, or research center leadership role: Vice Director, Cardiovascular Disease Research Institute, Tianjin Chest Hospital; Director, Biobank, Tianjin Chest Hospital
- Membership in an international academic organization: Fellow of the American College of Cardiology (FACC); Fellow of the European Society of Cardiology (FESC)
- Editorial role at an academic journal: Editorial board member or peer reviewer for Chinese Journal of Cardiology, Tianjin Medical Journal, and more than 20 SCI-indexed journals
- Major publication record or other academic achievement: Principal investigator or co-investigator on 27 national, ministerial, and bureau-level key research programs; more than 60 oral presentations and chair roles at top international meetings (ACC, ESC, AHA, TCT); First recipient of Tianjin Science and Technology Progress Award (Second Prize); more than 120 academic publications; 65+ master’s and doctoral trainees supervised
 Fig. 1. Prof. Jing Gao at the ESC Venue
 Fig. 2. On-site Presentation Slide
Research Design: Focusing on the Special Population of Premature Myocardial Infarction
The study enrolled 1220 PMI patients who underwent percutaneous coronary intervention (PCI) between January 2017 and December 2024 (men ≤45, women ≤55). Using a baseline plasma homocysteine (Hcy) cutoff of 15 μmol/L, patients were divided into an elevated-Hcy group (≥15 μmol/L) and a normal-Hcy group (<15 μmol/L). The primary endpoint was a composite of major adverse cardiovascular events (MACE), including cardiac death, rehospitalization for worsening heart failure, non-fatal myocardial infarction, ischemic stroke, rehospitalization for unstable angina, and target-lesion revascularization. The median follow-up was 582 days (approximately 19 months), with a cumulative MACE incidence of 11.1% (136/1220). The study also collected body mass index (BMI), D-dimer, lipoprotein(a) (Lp(a)), and high-sensitivity C-reactive protein (hs-CRP) to evaluate the independent prognostic effect of Hcy and its joint effects with these markers.
Core Findings: Hcy’s Independent Predictive Value and “Risk-Multiplication” Effect
After full adjustment for traditional risk factors, elevated Hcy remained independently associated with MACE risk, with an adjusted hazard ratio (aHR) of 2.72 (95% CI: 1.87-3.95, P<0.001). This suggests that among PMI patients receiving standard PCI and secondary prevention, those with elevated Hcy have a significantly higher MACE risk—approximately 2.72-fold.
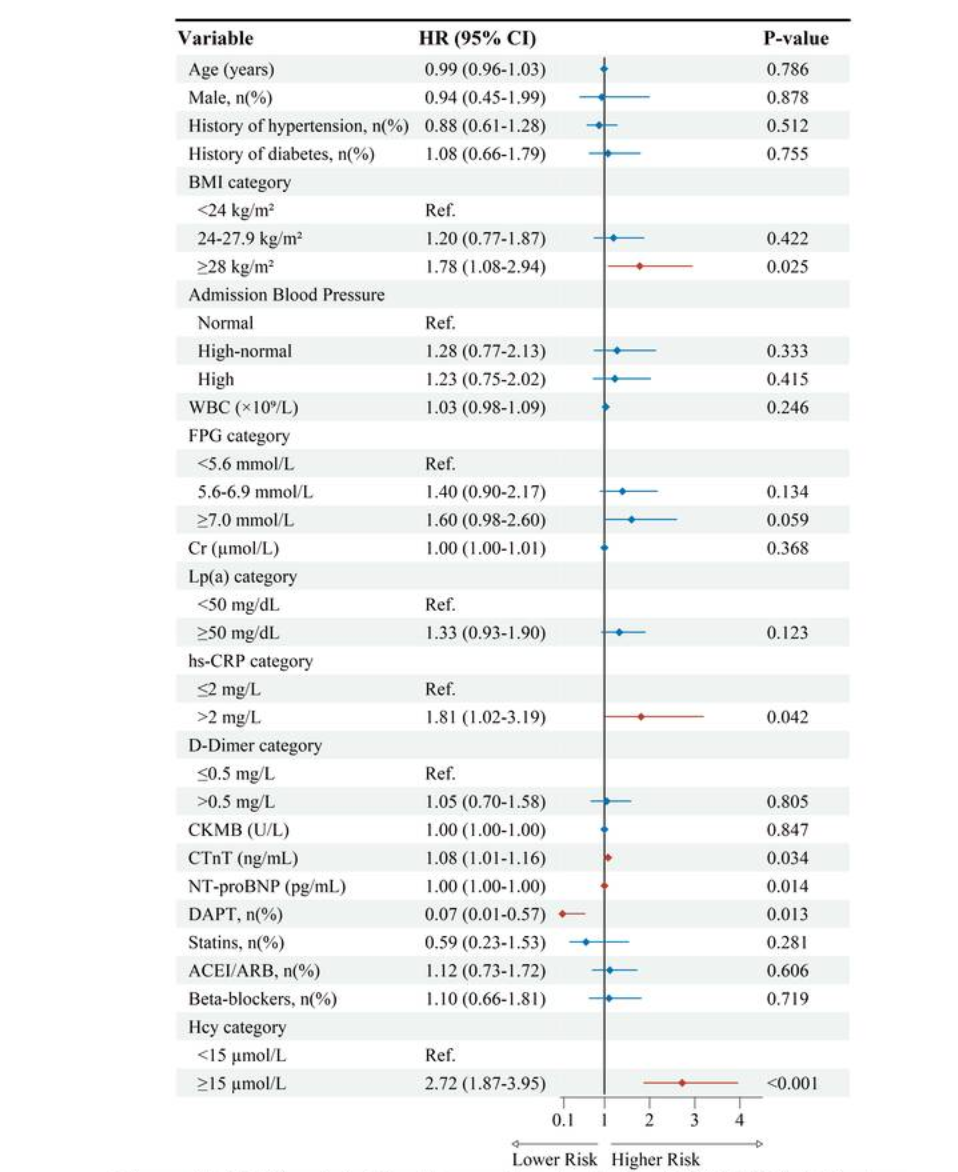 Fig. 3. Forest Plot of Multivariable Cox Regression Analysis for MACE in PMI Patients
Of greater clinical concern, Hcy showed a marked synergistic amplification effect with other metabolic and inflammatory risk factors. Multivariable Cox regression analysis showed that when elevated Hcy was combined with elevated D-dimer (>0.5 mg/L), elevated Lp(a), or elevated hs-CRP (>2 mg/L), MACE risk increased to 3.13- to 4.12-fold that of the normal-Hcy group. When elevated Hcy coexisted with obesity (BMI ≥28 kg/m²), the risk escalated further to 6.54-fold (aHR=6.54, 95% CI: 3.01-14.20, P<0.001). Kaplan-Meier survival curves visually corroborated this synergistic effect: in subgroups with elevated Hcy combined with other positive risk factors (Fig. 4A-D), the MACE-free survival curves showed a pronounced cliff-like decline (P<0.0001).
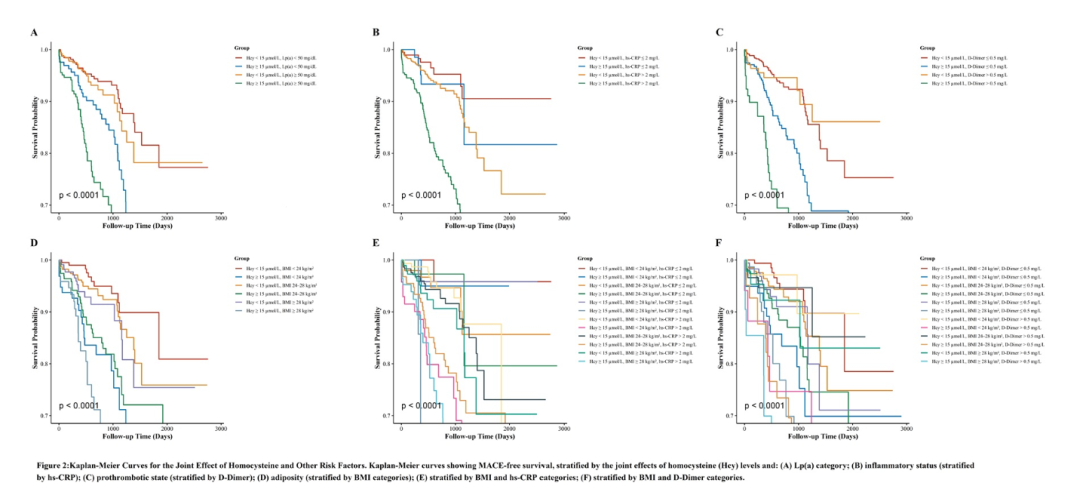 Fig. 4. Kaplan-Meier Survival Curves of the Synergistic Effects between Hcy and other Risk Factors
Further three-factor joint analyses revealed a non-linear risk accumulation: when high Hcy, obesity, and elevated D-dimer were all positive, MACE risk rose to nearly 10-fold (aHR=9.91, 95% CI: 3.68-26.66, P<0.001); when high Hcy, obesity, and elevated hs-CRP were all positive, the risk climbed to 17.51-fold (aHR=17.51, 95% CI: 2.28-134.52, P=0.006). The corresponding survival curves (Fig. 2E, F) also showed that the multi-risk-factor group had the steepest decline. Although the confidence interval for the high-Hcy + obesity + high-hs-CRP group is wide—reflecting the relatively small sample size in that specific subgroup—the large effect size, statistical significance, and consistent direction of the survival curve trend suggest the finding is robust.
Conclusion
These findings have clear clinical translational value. First, the independent predictive effect of Hcy on MACE (aHR=2.72) approaches or exceeds that of some traditional risk factors, suggesting that in the secondary prevention of PMI patients, Hcy should be incorporated into routine risk assessment rather than being treated as a “marginal” marker. Second, PMI patients with elevated Hcy combined with obesity or elevated inflammatory markers show risk multiplication rather than simple additive risk and warrant more intensive follow-up and more aggressive secondary prevention strategies. Third, Hcy is a modifiable metabolic target, and folic acid and B-vitamin supplementation can effectively reduce its levels. Although previous large randomized controlled trials have produced mixed results on the benefit of Hcy-lowering therapy, the high-risk subgroups identified in this study (e.g., Hcy elevation + obesity + high hs-CRP, with a 17.5-fold increased risk) may represent the populations most likely to benefit from Hcy-lowering therapy, providing a precision direction for future mechanism-driven nutritional intervention strategies. Furthermore, the validation of 15 μmol/L as a risk-stratification cutoff in this population provides clinicians with a simple, low-cost reference tool.
Of course, this study has limitations. It is a single-center design; although the sample size (1,220 patients) is relatively large in the premature MI field, the three-factor joint subgroup sizes are limited, leading to wider confidence intervals for some effect estimates, which will need validation in larger samples. The median follow-up of only 19 months is insufficient to evaluate Hcy’s impact on very long-term prognosis. In addition, Hcy testing has not yet been standardized, and comparability across laboratories needs improvement. Future multicenter studies are warranted to validate these findings, evaluate the benefit of Hcy-lowering therapy in the high-risk subgroups identified, and explore the joint risk-stratification value of Hcy with other novel biomarkers to construct more accurate prognostic prediction models for PMI patients.
Expert Profile:
Dr. Jingyu Liu

- Current academic and clinical title, department, and institution: Associate Chief Physician, Tianjin Chest Hospital
- Major publication record or other academic achievement: Long-term clinical and research work in coronary heart disease and critical cardiovascular care; expertise in early identification, risk assessment, and comprehensive management of acute MI, acute coronary syndrome, and cardiogenic shock; research focus on screening and clinical application of novel biomarkers in acute myocardial infarction, with attention to early warning, risk stratification, and individualized therapy; 7 academic publications (1 first-author, 1 co-first-author); 1 oral presentation at an ESC scientific session
References:
[1] Gao J, Liu JY, Wang YH, et al. Homocysteine multiplies risks of adverse outcomes in premature myocardial infarction: synergistic effects with obesity and inflammation. Eur Heart J. 2026;44(Suppl_2). (ESC 2026 Abstract)

